Case Summary
A toddler presented with noisy breathing and intermittent stridor over the last few months associated with feeding difficulties. On physical examination, the patient had inspiratory stridor at rest with mild subcostal retractions and intermittent wheezing, while the cardiovascular exam was unremarkable with normal heart sounds.
Imaging Findings
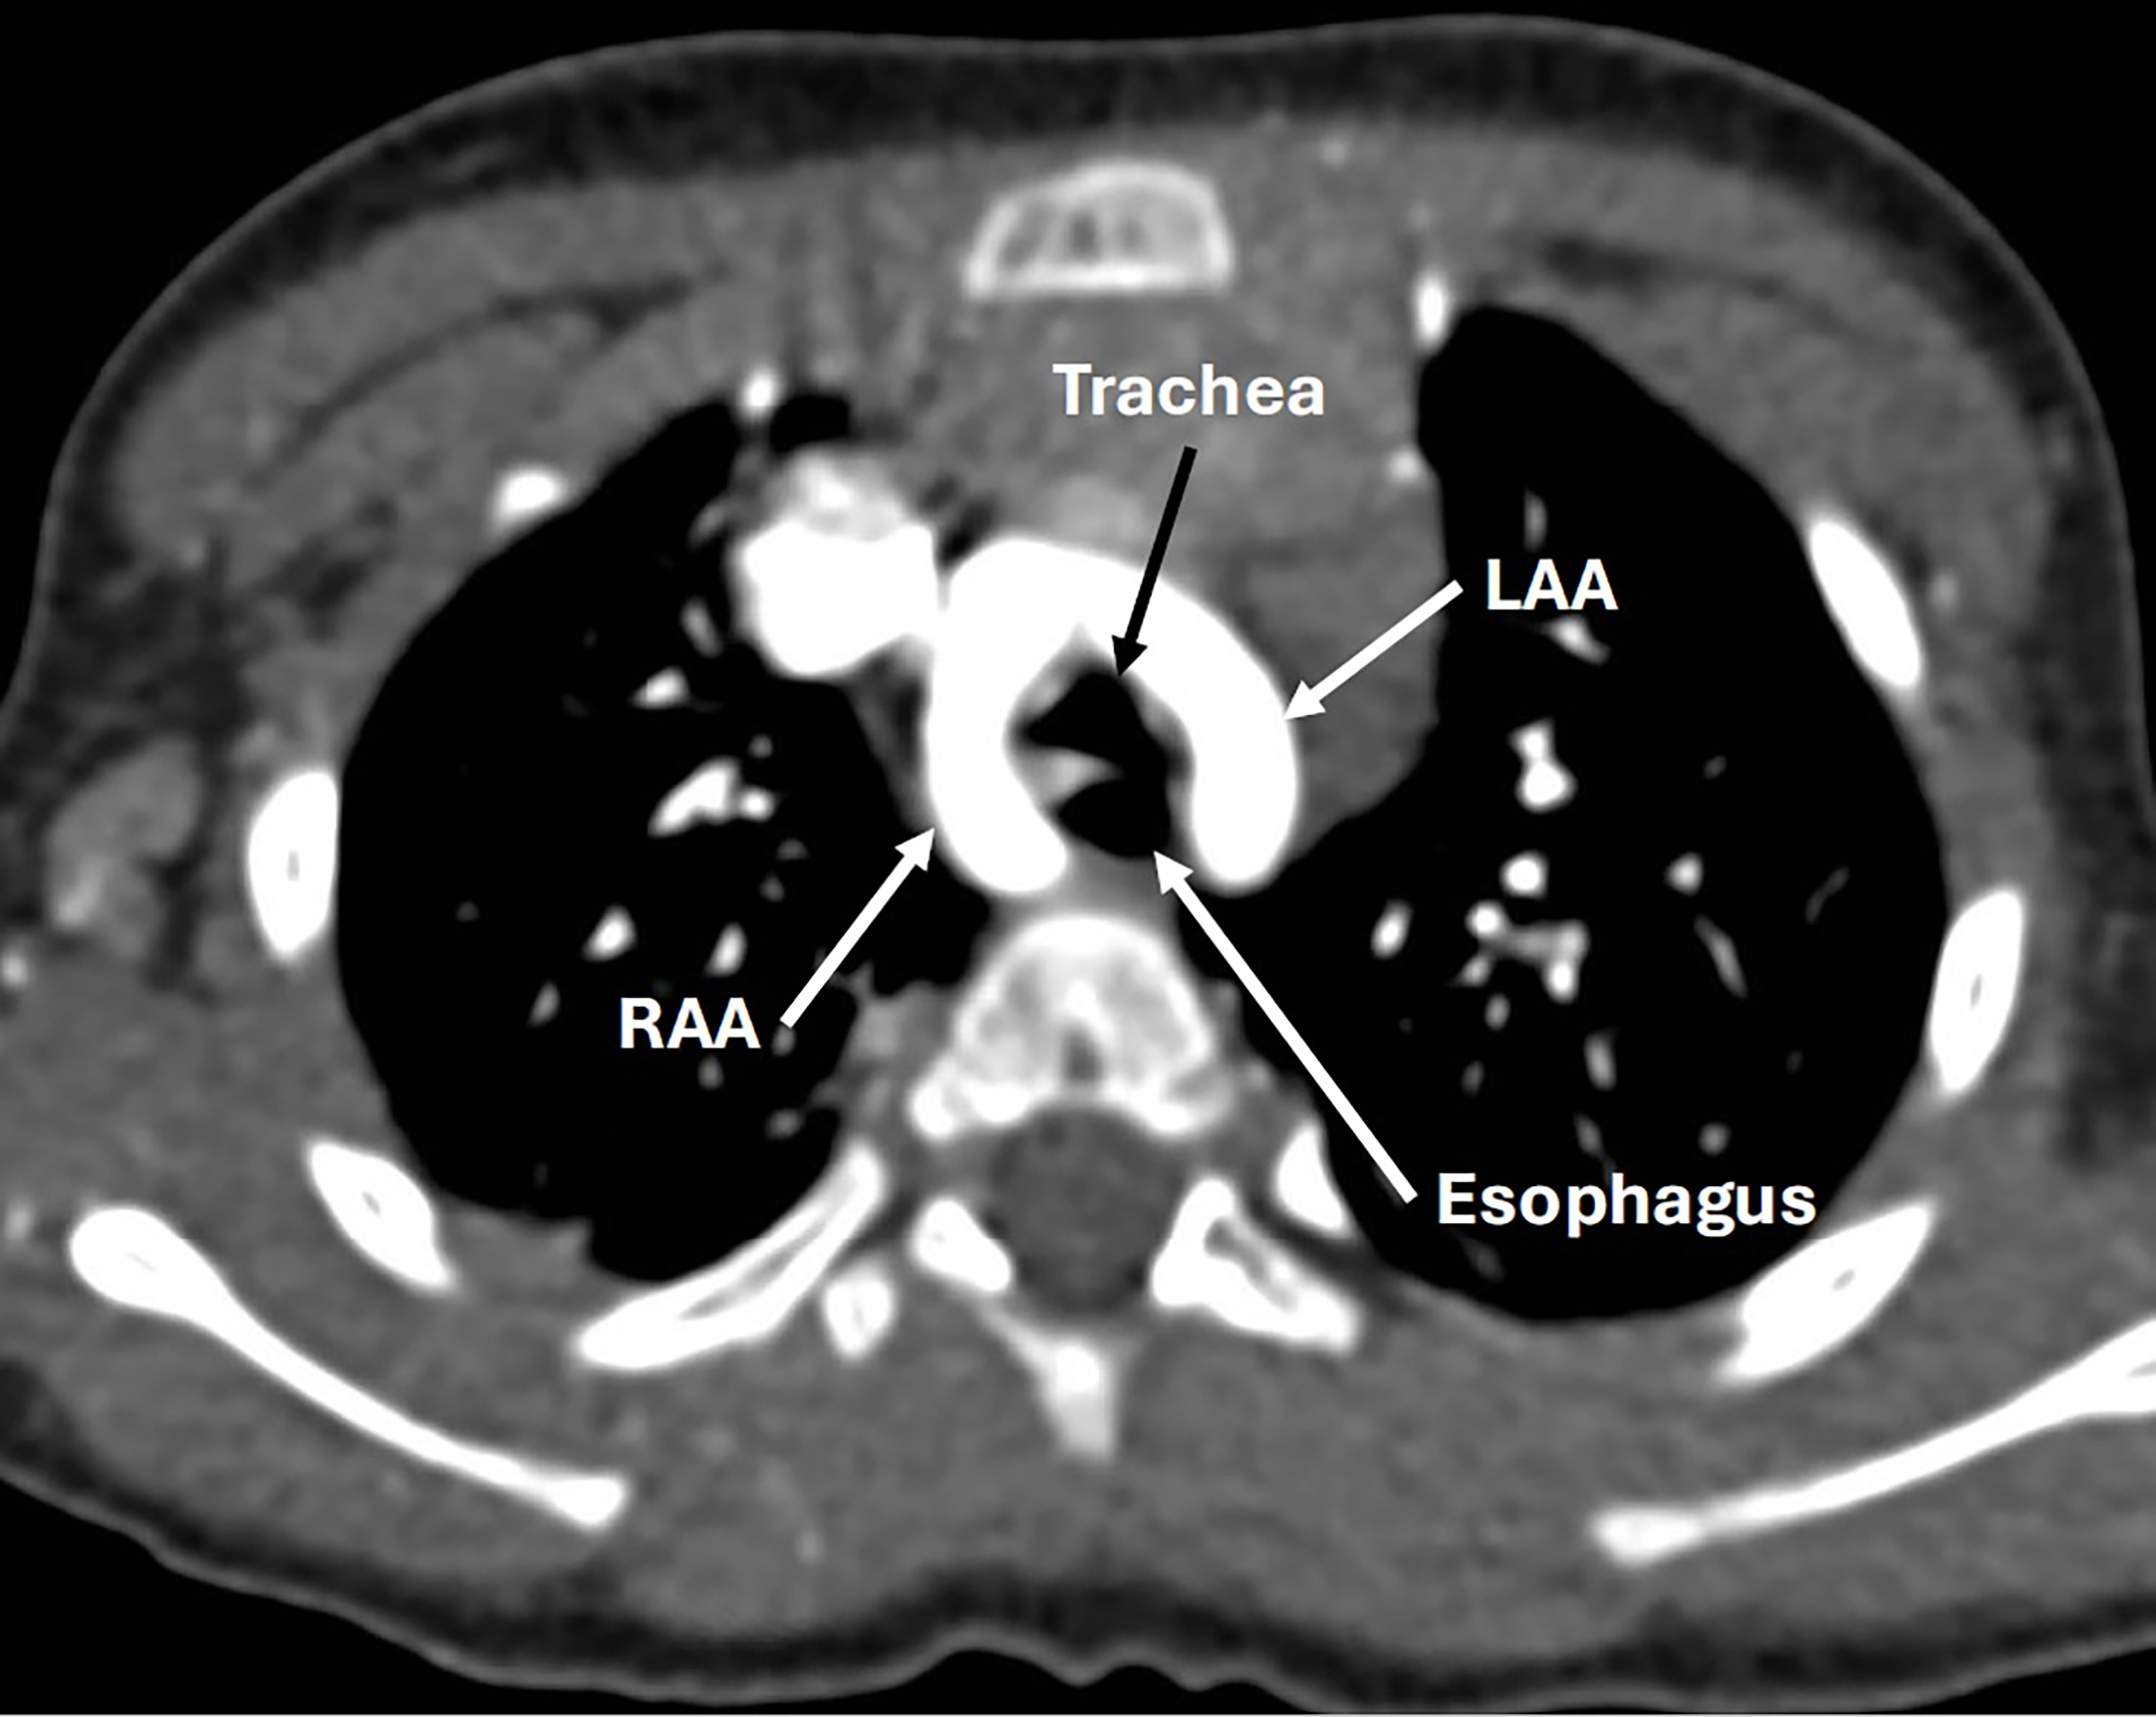
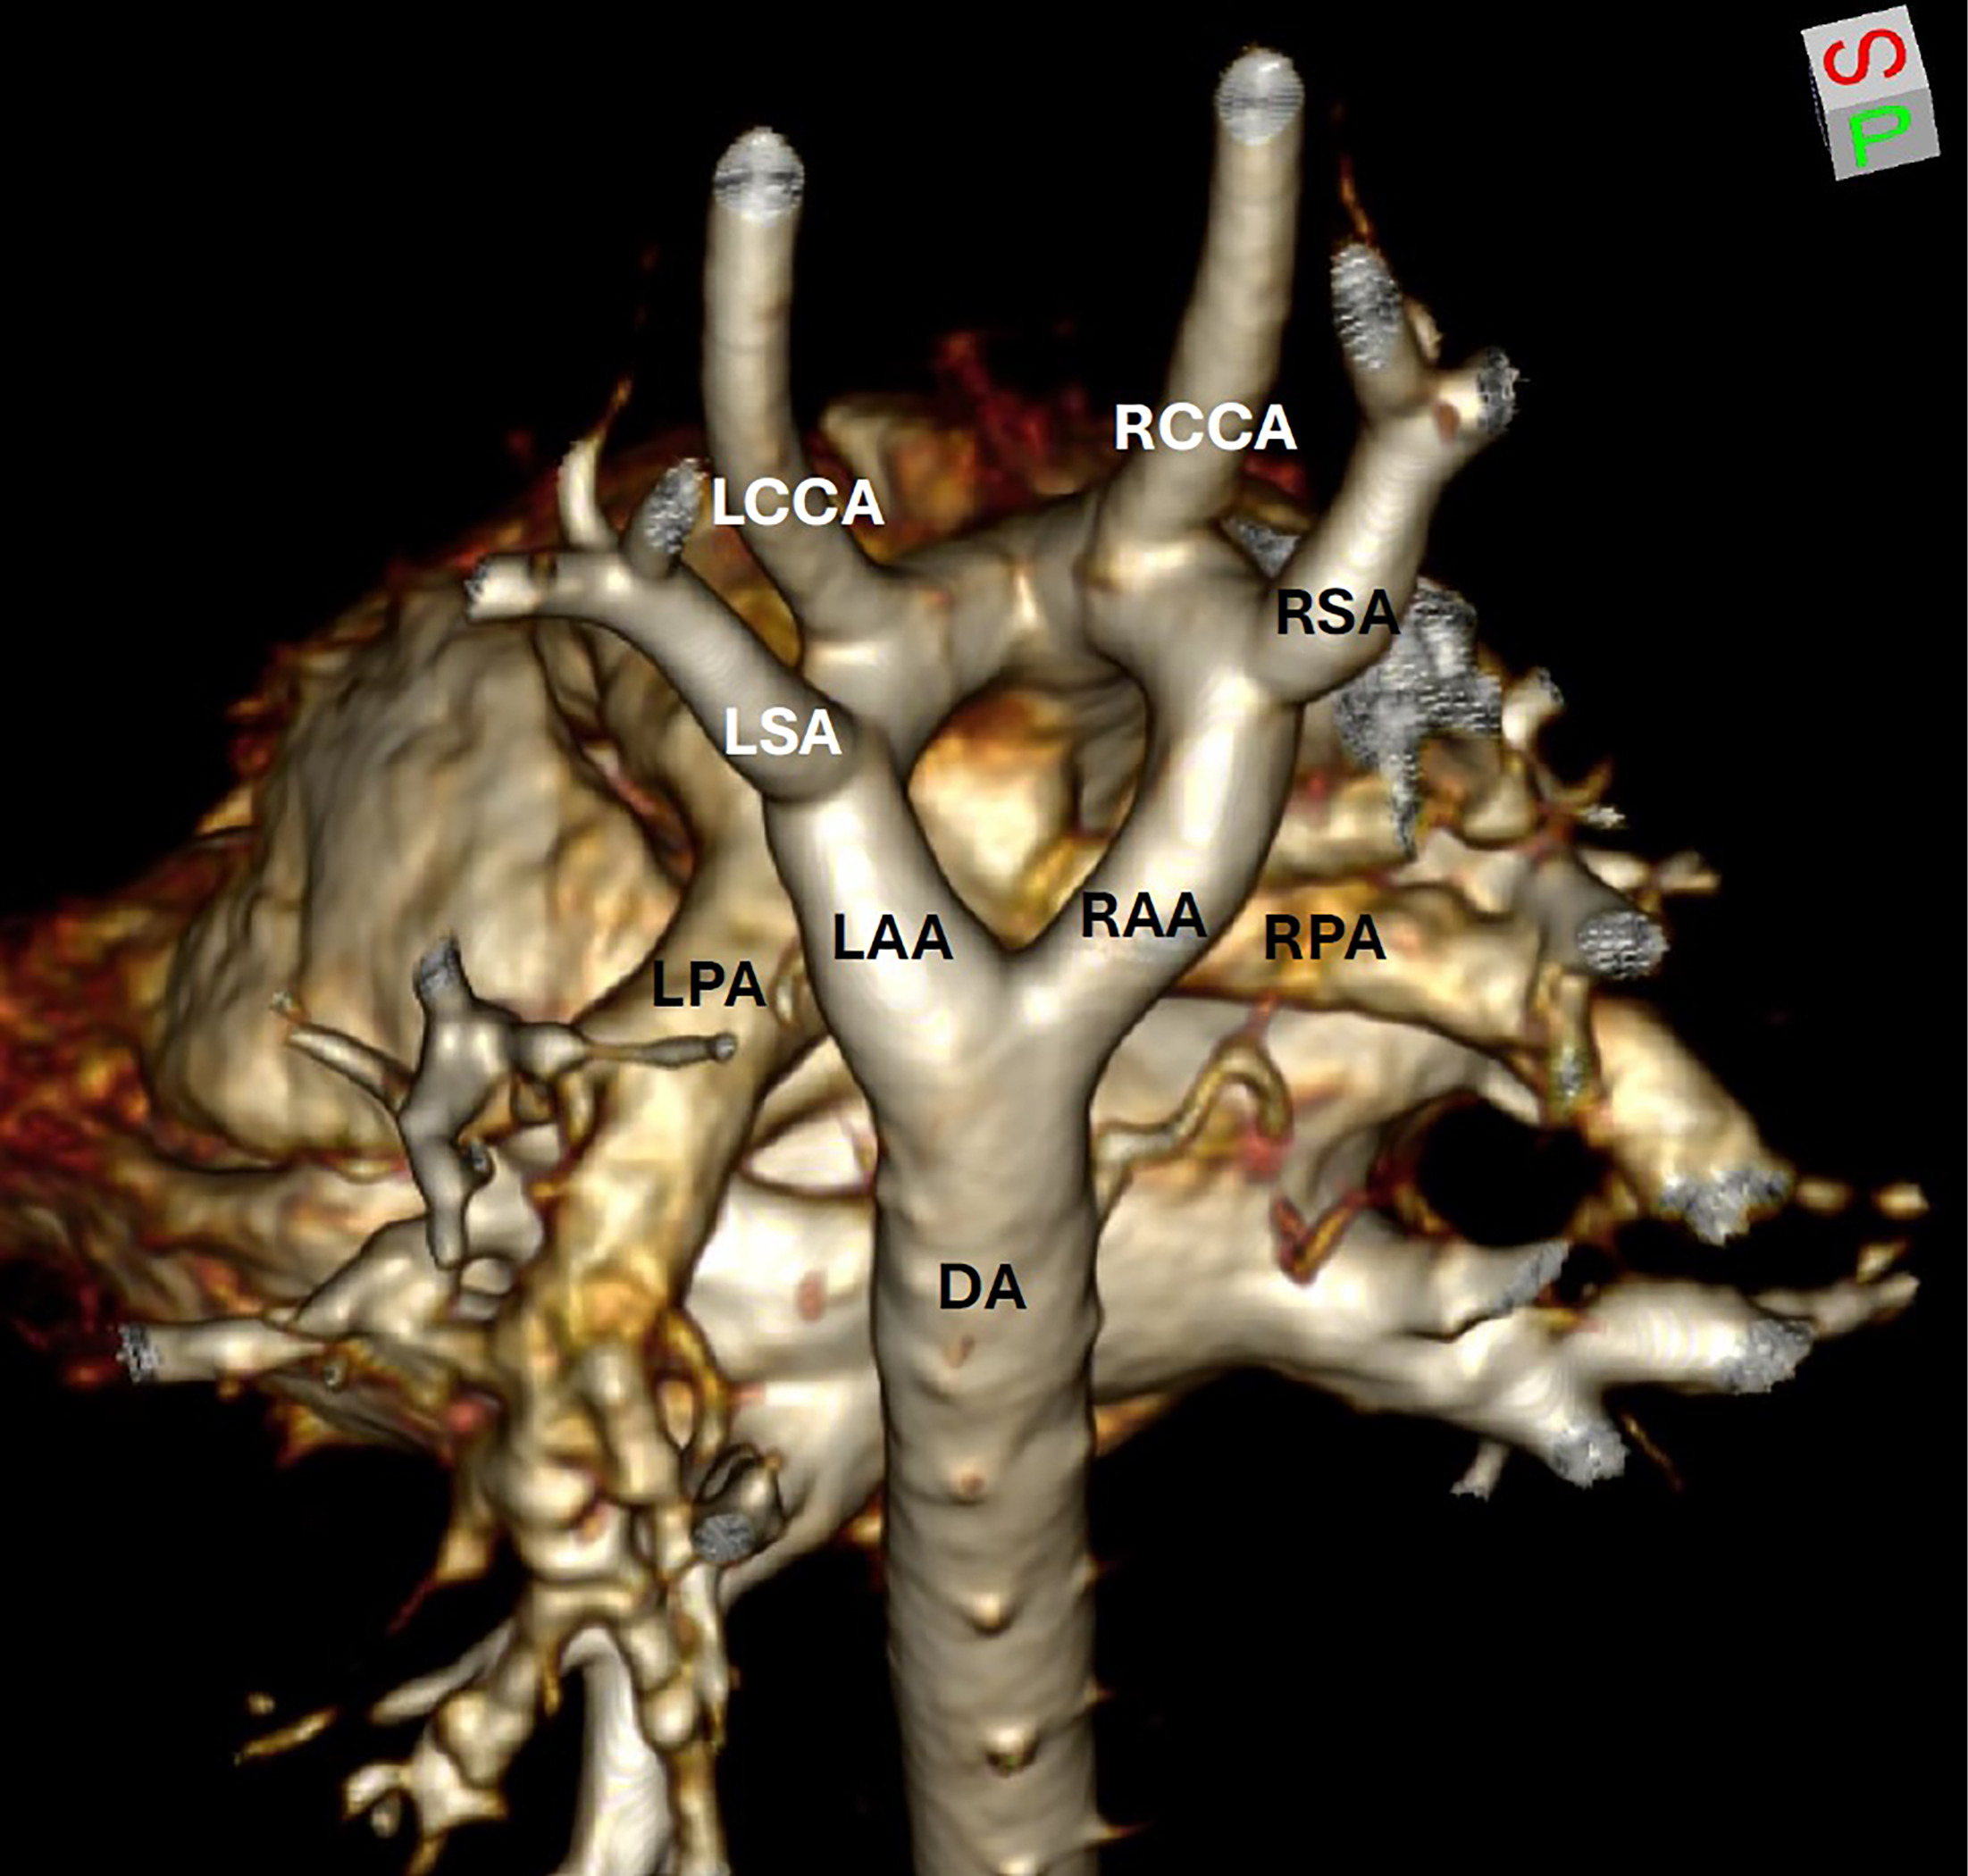
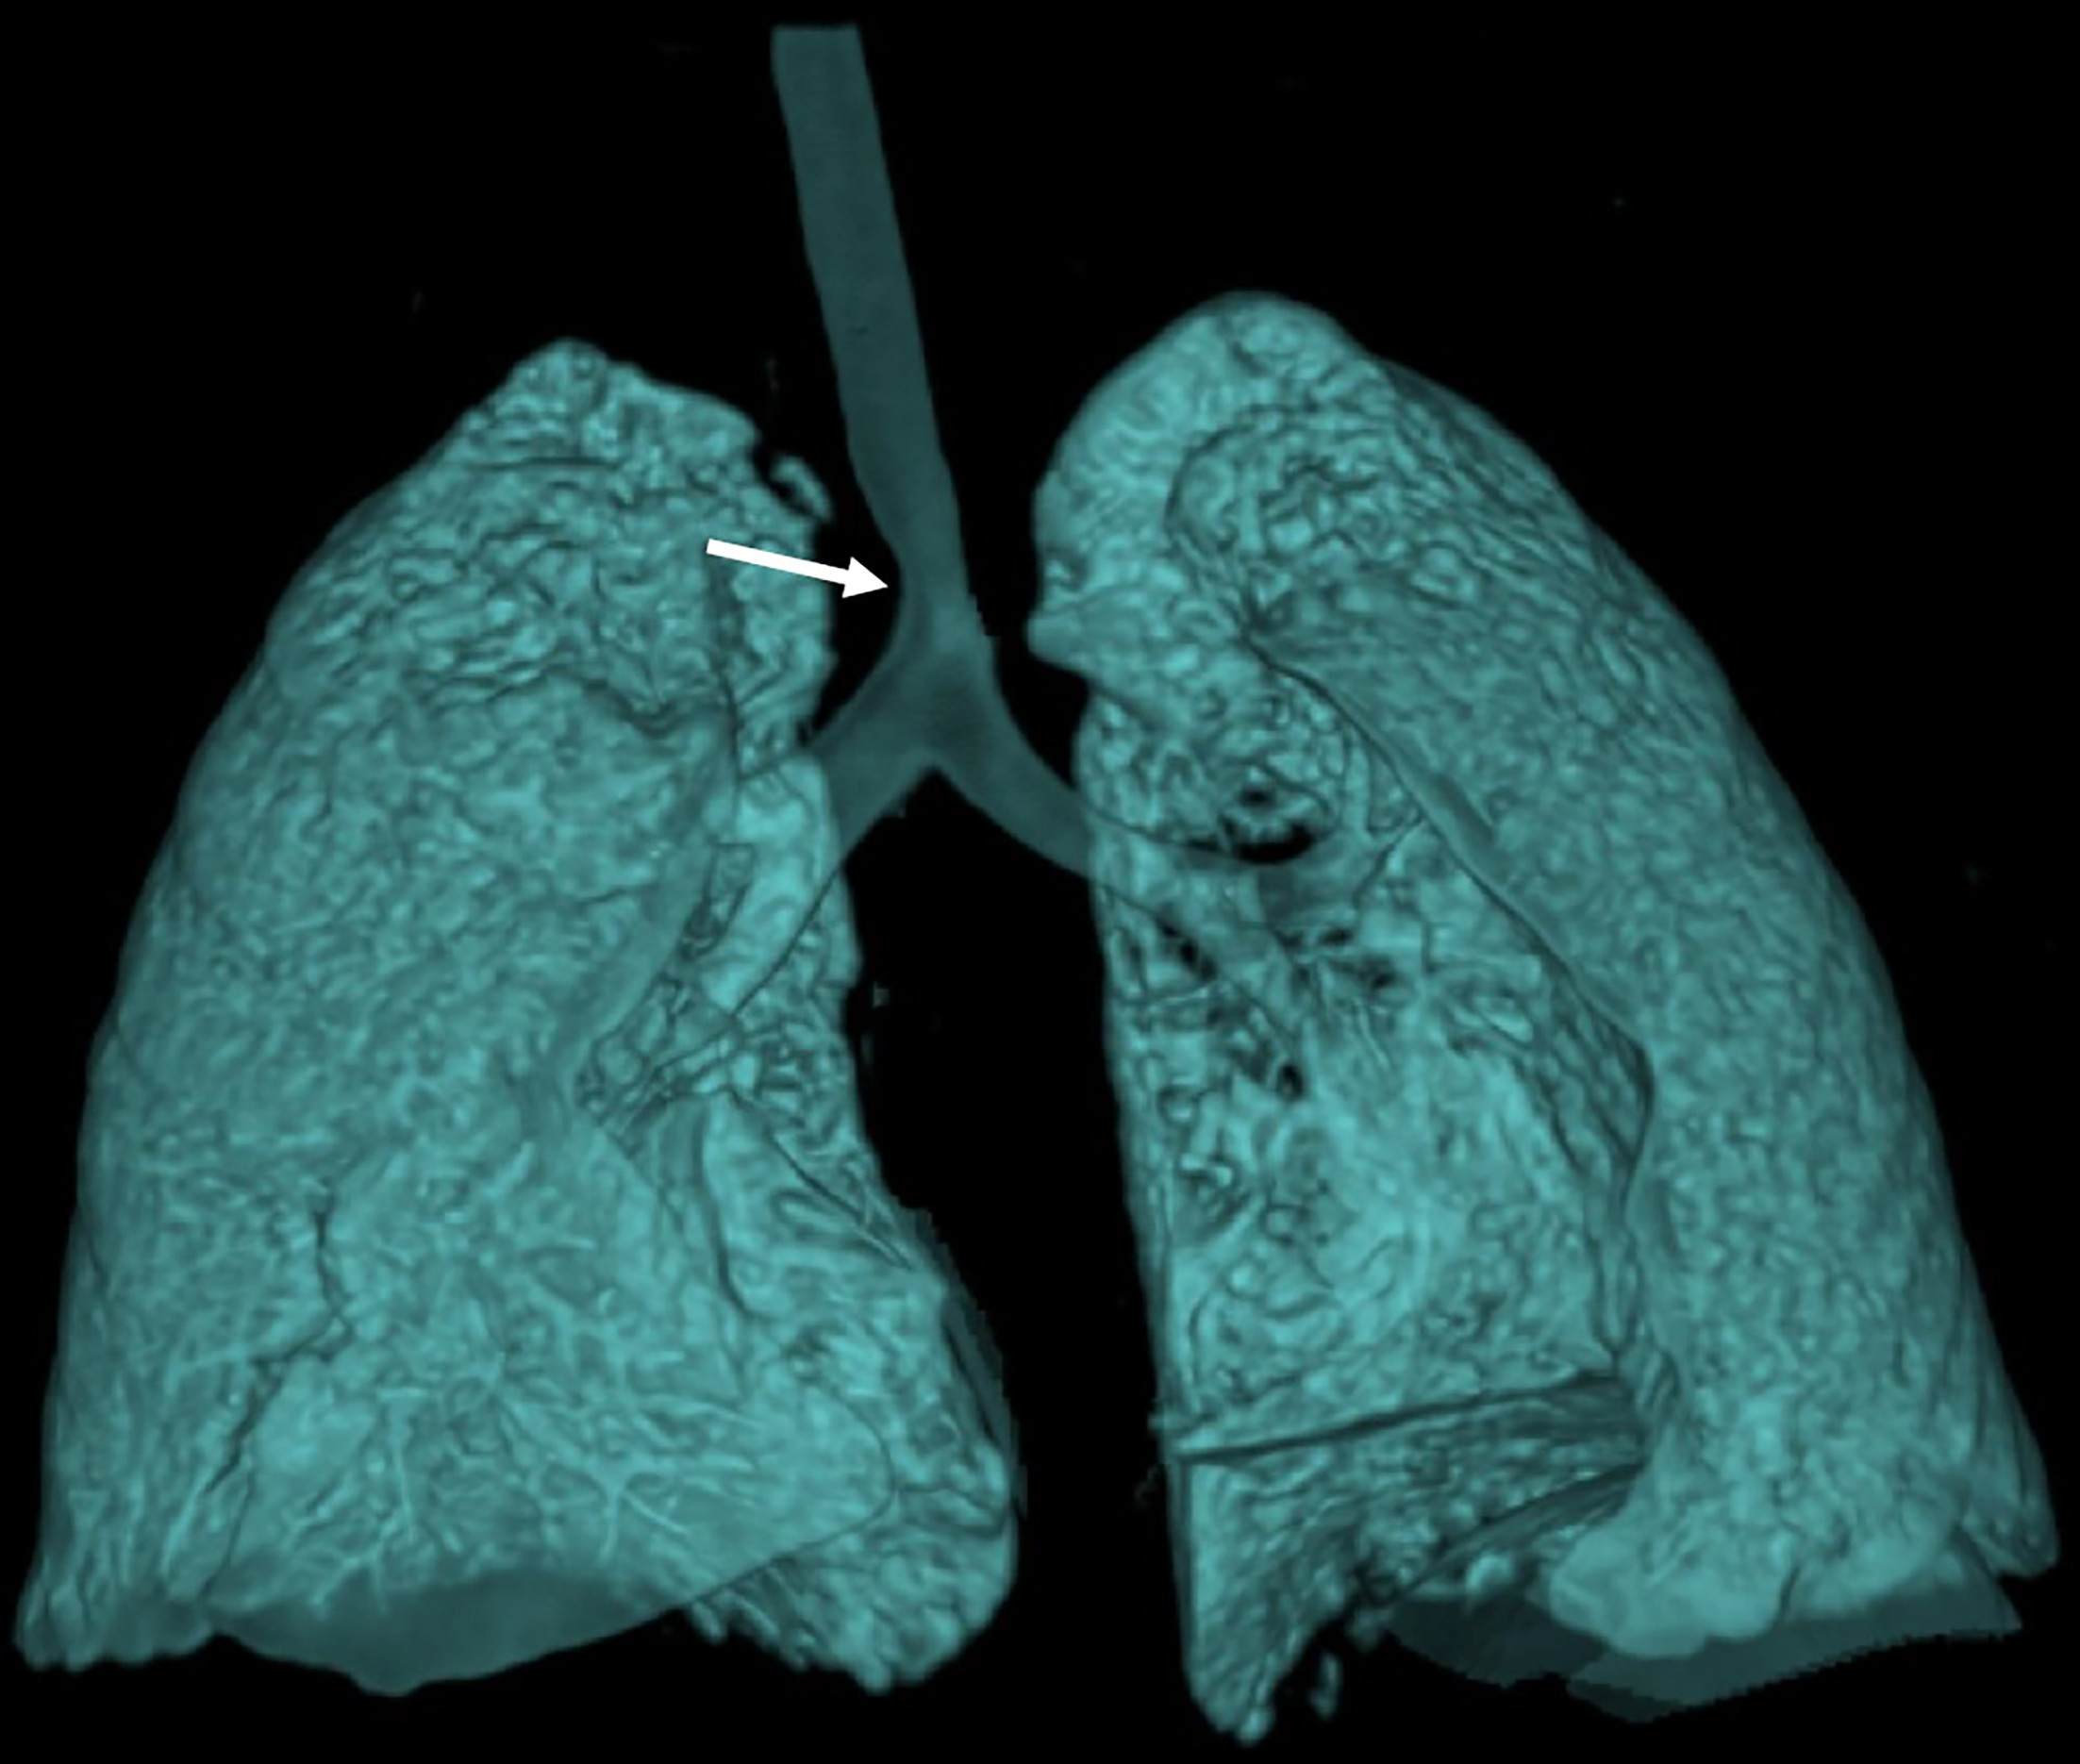
Chest CT with contrast (Figures 1-4) showed a double aortic arch (DAA) with the same-size left and right aortic arches. There was narrowing of the distal trachea and mid esophagus (Figures 3, 4) at the level of the DAA.
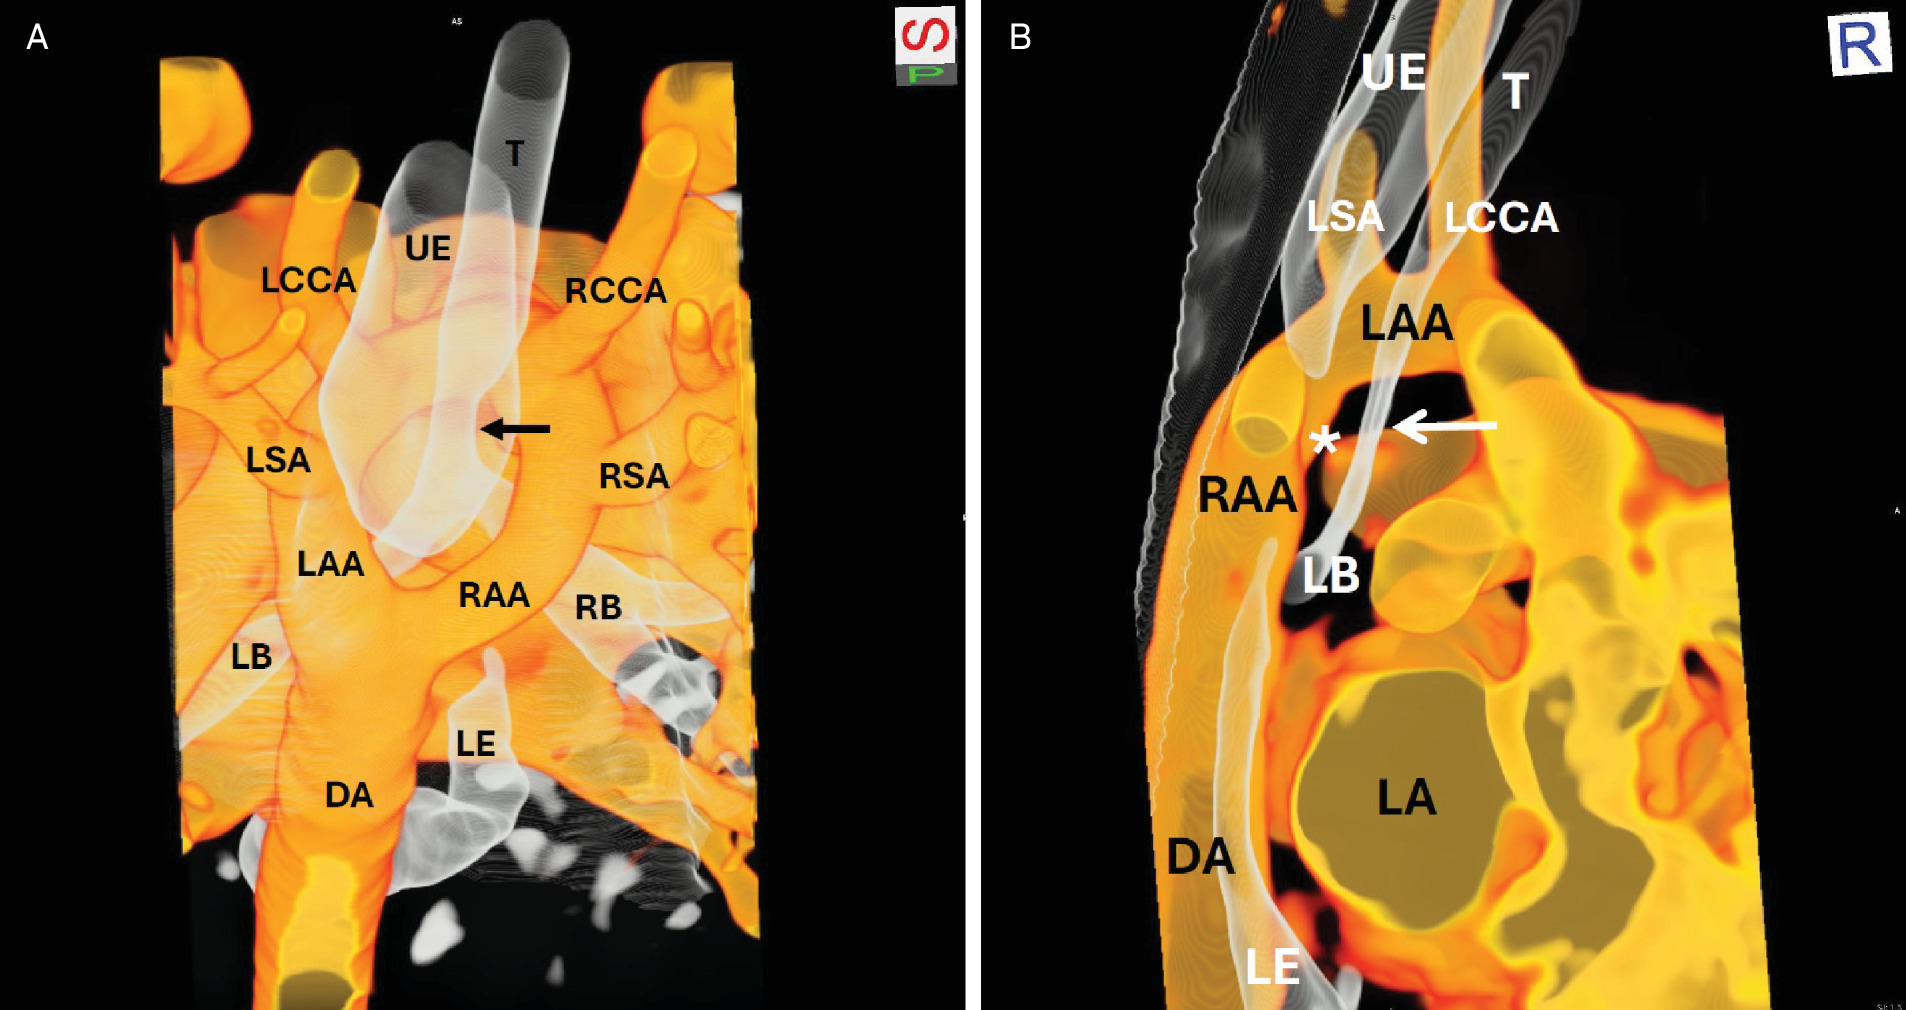
Diagnosis
Double aortic arch.
Differential diagnostic considerations based on the clinical findings are tracheomalacia, laryngomalacia, laryngeal web, laryngeal cyst, mediastinal mass (lymphoma), tracheoesophageal fistula, asthma, gastroesophageal reflux disease, bronchiolitis, and recurrent lower respiratory tract infection. Imaging-based differential diagnosis includes a right aortic arch with an aberrant left subclavian artery, pulmonary artery sling, brachiocephalic artery compression, and mediastinal masses.
Discussion
Vascular rings are congenital abnormalities of the embryological aortic vessels, which may surround the trachea and/or the esophagus and lead to compression of adjacent structures. These vascular ring anomalies have been described as early as 1737 by Hommel, with descriptions of tracheal and esophageal obstruction being described in 1837 by von Siebold.1 Development of the aortic arch occurs between weeks 2 and 7 of gestation, during which 6 pairs of primitive aortic arches form, and certain arches involute to form the normal left-sided aortic arch. Arches 1 and 2 regress, leaving the hyoid, maxillary, and stapedial arteries, while arch 3 forms the common carotid and part of the internal carotid arteries. The 4th pair of aortic arches forms bilateral aortic arches, after which the right-sided arch regresses in week 5 of gestation, with the left-sided aortic arch remaining.2
While multiple variants of vascular rings exist with complete, partial, or atretic segments, the most common is the DAA in which there is complete encirclement of the esophagus and trachea. There are 3 main types of DAA: left dominant, right dominant, and co-dominant arch. The true incidence of the DAA is not well established; however, data from a 20-year single-center study found the incidence of all aortic arch anomalies to be 0.033% and all ring-forming anomalies to be 0.021%.3 In children with DAA, the median maternal age was higher, the incidence of conceptions from in vitro fertilization was higher, and the incidence of DAA in 22q11 deletions was 14%.4,5
As the anatomy of DAA anomalies may have multiple variations, the presentation depends on the degree of compression of the trachea and esophagus. Presenting symptoms can range from acute manifestations of tracheal/esophageal compression to subtle subacute signs. In general, esophageal compression in children with DAA may present with persistent dysphagia, choking, regurgitation, and potentially failure to thrive. With respect to tracheal compression, children may present with acute signs of respiratory failure, cyanosis, and apneic episodes, or more subtle signs such as wheezing, stridor, persistent cough, and recurring lower respiratory tract infections.2 Findings on physical exam and laboratory tests are generally nonspecific but may be helpful in ruling out other potential causes.
Echocardiography, cardiac MRI, CTA, and barium esophagrams may all be useful in the diagnosis of vascular rings. Transthoracic echocardiography may be the initial imaging modality used due to it being minimally invasive and the lack of radiation exposure. On the other hand, the complexity of certain vascular anomalies will likely require MR angiography or CTA for adequate visualization, especially in the presence of life-threatening sequelae.6 The disadvantage of MR angiography is the longer acquisition times likely requiring sedation of pediatric patients, while for CTA, it is the pediatric exposure to radiation. Many with DAA go undiagnosed or may incidentally be found during various forms of imaging. Vascular rings may be found incidentally during barium esophagram, evaluating the potential causes of dysphagia. Similarly, tracheal compression may be found incidentally during bronchoscopy for the evaluation of respiratory symptoms.
The first documented surgical repair of a vascular ring was described in 1947, and the current standard treatment for most DAA cases remains to be surgical intervention, with the goal of releasing the compression on the trachea and/or the esophagus.2,7 Generally, the approach is via a muscle-sparing thoracotomy on the nondominant side. The surgery involves entering the chest cavity, identifying important structures such as the vagus and phrenic nerves, occluding the nondominant arch, and lastly dividing the nondominant arch and ligamentum arteriosum.2,5,8 In the case of a co-dominant arch, the posterior arch is resected to preserve a more anatomic structure. Surgery is largely successful (95-98%), with most patients undergoing DAA repair having good prognoses. Follow-up after surgery tends to yield relatively mild respiratory or gastrointestinal symptoms, likely related to compression-related maldevelopment.
Conclusion
DAA is a congenital vascular anomaly of the primitive aortic arches that leads to compression of the trachea and/or the esophagus. Children with a DAA usually present with nonspecific signs of tracheal/esophageal compression such as dysphagia, cough, respiratory failure, and choking. Consequently, vascular rings such as the DAA are often found incidentally on imaging and may be further evaluated using transthoracic echocardiography, MR angiography, or CTA. Management of symptomatic cases of DAA involves surgical repair in which the nondominant branch is resected, leading to an excellent prognosis and survival.